

We use cookies to ensure our website works properly and to personalise your experience. Cookies policy
1,3,4Department of Pharmacy, Shri Swami Samarth Institute of Pharmacy, Malwadi Bota.
2Department of Pharmaceutical Chemistry, Shri Swami Samarth Institute of Pharmacy, Malwadi Bota.
Absrtact: Quality is a central requirement in pharmaceutical products because medicines must consistently meet predefined standards of identity, strength, purity, safety and performance. Quality Control (QC) provides sampling, testing and analytical evidence about materials and products, while Quality Assurance (QA) builds a documented system that prevents errors and ensures that work is performed according to approved procedures. This review synthesises key principles across the major areas of a pharmaceutical QC–QA curriculum: good practices and pharmaceutical quality systems; testing of raw materials, packaging components, in-process samples and finished dosage forms; regulatory authorities and drug-development submissions; documentation and data integrity; qualification, calibration and validation; cleaning and analytical-method validation; Quality by Design (QbD), Process Analytical Technology (PAT), audits and intellectual-property basics. International guidance from WHO, ICH and the US FDA is considered alongside the Indian regulatory context. The literature and guidance indicate that reliable quality depends on a lifecycle approach rather than end-product testing alone. Risk-based decisions, trained personnel, suitable facilities, validated processes, trustworthy data, change control and continual improvement work together to reduce patient risk. Implementation challenges include resource constraints, fragmented data systems, weak investigations, supplier variability and the need to maintain consistent standards across sites and markets. The review concludes that an integrated quality culture linking QC, QA, manufacturing, regulatory affairs and management is essential for dependable medicines and sustainable compliance.
The aim of this review is to present a connected overview of pharmaceutical QC and QA aligned to the supplied syllabus. Objectives are to explain the role of GMP and good laboratory practice; summaries testing across the product lifecycle; describe key regulatory bodies and submissions; discuss controlled documentation and data integrity; compare calibration, qualification and validation; outline process, analytical and cleaning validation; and explain QbD, PAT, audits and intellectual-property concepts.
This educational review uses a narrative synthesis of major public regulatory guidance and recognized quality frameworks, including WHO GMP principles, ICH quality guidelines, and FDA guidance on process validation, PAT and analytical procedures. It is not a systematic review: no exhaustive database search, formal screening protocol, meta-analysis or risk-of-bias assessment was performed. Statements are paraphrased and sources are identified in the references. The exact legal applicability of a guideline depends on jurisdiction, product type and the current version adopted by the relevant authority.
The scope spans the modules visible in the supplied syllabus, including GMP and Q-series guidelines, dosage-form testing, regulatory authorities, documentation, drug development and applications, qualification and validation, cleaning validation, QbD/PAT, audits and intellectual property. Because the supplied screenshots do not show every syllabus page, the paper uses a broad curriculum-aligned structure rather than claiming to reproduce every individual topic word-for-word.
Quality should be viewed as a system outcome. Product quality depends on the suitability of the formulation, quality of starting materials, reliability of the manufacturing process, accuracy of analytical methods, packaging performance and storage conditions. A weakness in any one element can affect the final product. For this reason, pharmaceutical companies use defined responsibilities, written procedures and independent checks to reduce avoidable variation.
An effective quality system also supports business continuity. Preventing defects can reduce rejected batches, rework, investigations, regulatory observations and shortages. The cost of prevention is often lower than the cost of a major quality failure. However, commercial benefits must never override the primary objective of protecting patients. Quality decisions should be based on evidence and documented scientific reasoning.
1. QUALITY CONTROL, QUALITY ASSURANCE AND GMP
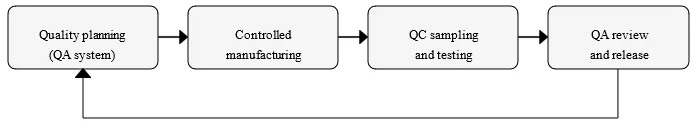
.1Relationship between QA, manufacturing, QC testing and feedback.
1.1 Core concepts
QC is product- and data-focused: it confirms whether samples meet established specifications using approved methods and suitable equipment. QA is system-focused: it establishes and monitors the procedures that make quality likely and prevents defects where possible. QC may reject a nonconforming batch, but QA ensures that the event is investigated, its impact is assessed, corrective actions are implemented and recurrence is prevented. Neither department can ensure quality alone; manufacturing, engineering, warehousing, supply chain and senior management also carry responsibilities.
1.2 Good Manufacturing Practice
Good Manufacturing Practice (GMP) is the part of quality management that ensures products are consistently produced and controlled according to appropriate standards. Core GMP themes include qualified personnel; hygienic and suitable premises; qualified equipment; controlled materials; approved procedures; prevention of mix-ups and cross-contamination; complete records; investigation of deviations; and independent quality oversight. GMP requires activities to be performed as written and records to be completed when work occurs, not reconstructed later.
GMP is preventive. A final test examines only a sample and cannot detect every possible defect in a whole batch. For example, a non-uniform blend may produce tablets with variable content even if a limited number of tested tablets pass. Process control, validated mixing, in-process checks and suitable sampling are needed to control this risk. The same principle applies to sterility: a passing sterility test cannot compensate for poor aseptic practices or an uncontrolled sterilisation process.
1.3 GLP, cGMP and good warehousing
Good Laboratory Practice (GLP), in the context of routine quality laboratories, emphasises controlled methods, suitable facilities, qualified analysts, calibrated instruments, reference standards, traceable calculations and reliable records. The exact regulatory meaning of GLP differs by context; nonclinical safety-study GLP is a separate formal framework. Current Good Manufacturing Practice (cGMP) highlights that expectations evolve with scientific knowledge and regulatory requirements. Good warehousing practice includes defined storage conditions, segregation of quarantine/released/rejected materials, stock rotation, temperature monitoring, pest control, handling of returns and documented distribution.
1.4 ICH quality framework
ICH Q8 describes pharmaceutical development and supports understanding of product and process. ICH Q9 (R1) provides principles for quality risk management. ICH Q10 presents a pharmaceutical quality system across the product lifecycle. Together, these approaches connect development knowledge, risk-based controls and continual improvement. ICH Q2 (R2) and Q14 address analytical procedure validation and development. Their value lies in harmonizing scientific expectations while allowing justified, product-specific decisions.
GMP implementation requires control of the whole manufacturing environment. Personnel should follow hygiene and gowning requirements appropriate to their work. Equipment should be cleaned, maintained and labelled with its status. Materials should be identified and protected from mix-ups. Production areas should have appropriate flows and segregation. Written instructions should define processing steps, while records demonstrate that those steps were followed.
Deviation management is an important GMP element. When an unexpected event occurs, the organisation should record it promptly, assess the possible effect on the batch and other batches, determine the root cause and define appropriate action. Repeated deviations can indicate a weak procedure, inadequate training, unsuitable equipment or an ineffective control strategy. Management should review recurring trends rather than treating every event as isolated.
2. QUALITY IN PHARMACEUTICAL INDUSTRY
Quality in the pharmaceutical industry means the ability of a medicine to meet predefined requirements and remain suitable for its intended use. These requirements are established through product development, pharmacopeial standards, approved specifications, regulatory submissions and applicable GMP requirements. Quality includes more than a satisfactory laboratory result; it also includes reliable manufacturing, suitable packaging, correct labelling and controlled distribution.
Important quality attributes include identity, strength, purity, potency, stability, dissolution, uniformity, microbial quality and, where relevant, sterility and endotoxin limits. The relevant attributes depend on the dosage form and intended route of administration. For example, tablets may require tests for weight variation, content uniformity, disintegration and dissolution. Sterile injections require additional controls for sterility, bacterial endotoxins, particulate matter and container-closure integrity.
2.1. The major elements that influence pharmaceutical quality are:
Quality failures may result in ineffective treatment, adverse reactions, product recalls, financial loss and loss of public confidence. Examples include incorrect active ingredient quantity, microbial contamination, degradation during storage, mix-ups of labels and packaging, or failure to maintain sterile conditions. GMP reduces risks by requiring suitable facilities, trained personnel, written procedures and documented evidence that operations are consistently performed.
A strong quality culture means that every employee understands that product quality is not the responsibility of the QA department alone. Operators must follow approved instructions, analysts must report genuine results, supervisors must review operations and management must provide sufficient resources. The organisation should encourage early reporting of problems instead of hiding errors.
2.2. Importance of QA and QC:
The importance of these functions becomes especially clear for sterile products, biologics, vaccines, modified-release products and other complex medicines. Such products may have critical quality attributes that cannot be fully assessed by a single finished-product test. Strong process understanding, suitable controls and lifecycle monitoring are therefore essential.
3. RESPONSIBILITIES OF QA AND QC IN PHARMACEUTICAL INDUSTRY
3.1. QA responsibilities:
1. Quality system: Establish, maintain and periodically review the pharmaceutical quality system.
2. Document control: Prepare, review, approve, issue and control SOPs, specifications, formats and other controlled documents.
3. Batch record review: Check manufacturing and packaging records for completeness, accuracy, deviations and compliance before batch disposition.
4. Deviation management: Ensure that deviations are reported, investigated, documented and assessed for product impact.
5. CAPA: Coordinate corrective and preventive actions and verify their effectiveness.
6. Change control: Assess proposed changes to materials, processes, equipment, facilities, documents and computerised systems before implementation.
7. Audits: Plan and conduct internal audits and coordinate supplier or external audits as appropriate.
8. Training: Ensure that employees receive initial and periodic GMP and job-specific training.
9. Validation oversight: Review and approve validation plans, protocols, reports and continued verification arrangements.
10. Complaints and recalls: Coordinate investigations of product quality complaints and support recall decisions and traceability.
11. Product release: Ensure that required records, results and quality checks are reviewed before authorised release.
12. Management review: Present quality trends and system performance to management.
3.2. QC responsibilities:
1. Sampling: Collect representative samples of raw materials, packaging materials, in-process materials and finished products according to approved procedures.
2. Material testing: Perform identity, assay, purity and other specified tests on incoming materials.
3. In-process testing: Examine samples collected during manufacturing to check critical parameters.
4. Finished-product testing: Perform the tests specified for the dosage form and product.
5. Microbiological testing: Conduct microbial limit, sterility, endotoxin and environmental tests where applicable.
6. Stability testing: Test samples at planned intervals to evaluate product quality during storage.
7. Instrument management: Use qualified and calibrated instruments and maintain instrument records.
8. Reference standards: Control reference standards, reagents, volumetric solutions and culture media as applicable.
9. Laboratory documentation: Record raw data, calculations, observations, chromatograms and final results accurately.
10. OOS/OOT reporting: Report out-of-specification and out-of-trend results promptly and support scientifically sound investigations.
11. Retention samples: Maintain required samples under specified conditions.
12. Reporting: Issue approved laboratory reports and communicate unusual results to relevant departments.
The exact division of duties varies according to the organization and applicable regulations. However, responsibilities, authority and independence must be clearly defined. No employee should change, omit or selectively report laboratory data to obtain a desired result.
4. QA AND QC WORK IN INDUSTRY
The daily work of QA and QC follows an organized flow. Before manufacturing begins, QA ensures that current approved documents, qualified equipment, trained personnel and appropriate material status are available. QC tests incoming materials according to approved sampling plans and specifications. Materials are identified and kept under suitable status controls until they are approved or rejected by authorized personnel.
During production, operators follow the batch manufacturing record and approved SOPs. In-process samples may be tested for parameters such as blend uniformity, granule moisture, tablet weight, hardness, thickness, friability, disintegration, pH or viscosity, depending on the dosage form. QC performs the assigned tests, while production and QA assess any unexpected result or process deviation. The objective is to detect process variation early and prevent defective material from progressing.
After manufacturing, QC tests finished-product samples against the approved specification. QA reviews the batch documentation, including material status, equipment records, line clearance, environmental or process records where applicable, deviations, laboratory results and packaging reconciliation. Batch disposition is made by the authorized quality function in accordance with applicable requirements.
4.1. A simplified industrial workflow is:
1. Supplier qualification and purchase of materials.
2. Receipt, quarantine, sampling and QC testing.
3. QA/QC-approved material status.
4. Dispensing and manufacturing under approved instructions.
5. In-process monitoring and testing.
6. Packaging, labelling and reconciliation checks.
7. Finished-product sampling and testing.
8. Batch record review and deviation assessment.
9. Authorised batch release or rejection.
10. Storage, distribution and post-market quality monitoring.
QA and QC also work on non-routine events. If a test result is outside specification, the laboratory follows an approved OOS procedure. If an operator finds an equipment malfunction, the event is reported and assessed. If a supplier changes a material source, change control evaluates the potential impact. If a complaint suggests a defect, QA coordinates investigation and evaluates whether a wider market action is needed.
Good communication is essential. QA, QC, production, engineering, warehouse and regulatory affairs should share relevant information promptly. Clear escalation pathways help ensure that potential risks are assessed before they affect patients.
5. COMMON TECHNIQUES OF QA AND QC
5.1. QA techniques are mainly system-based and preventive. Common methods include:
5.2. QC techniques are based on examination, measurement and testing. Common techniques include:
Statistical tools such as control charts, trend analysis, process capability analysis and sampling plans can support both QA and QC. These tools help distinguish normal process variation from unusual changes. The choice of technique should be scientifically justified and appropriate for the product, process and risk. A test should not be selected only because an instrument is available; it must be suitable for the intended purpose and supported by an approved method.
6. VALIDATION IN PHARMACEUTICAL INDUSTRY
Validation is the documented activity of establishing that a process, method, system or procedure consistently produces results meeting predetermined requirements. Qualification is generally used to demonstrate that facilities, utilities and equipment are properly designed, installed and operate as intended. Validation and qualification are essential elements of GMP and should be considered
throughout the relevant life cycle.
The purpose of validation is to provide documented evidence that critical activities are controlled and suitable for their intended purpose. It helps reduce variation, prevent failures, support reliable manufacturing and demonstrate compliance. Validation does not mean that a process can never fail; rather, it establishes a scientifically justified state of control that must be maintained and
periodically reviewed.
A typical validation programme includes:
1. Preparation of a validation policy or master plan.
2. Identification of systems, processes and methods requiring qualification or validation.
3. Risk assessment and definition of acceptance criteria.
4. Preparation and approval of protocols.
5. Execution by trained personnel using approved procedures.
6. Recording of observations, results and deviations.
7. Evaluation of results against predefined acceptance criteria.
8. Preparation and approval of a final report.
9. Establishment of routine monitoring and periodic review.
Validation should be proportionate to risk and supported by scientific knowledge. Changes to equipment, materials, process parameters, software or facility design may require impact assessment and partial or full requalification or revalidation. Continued process verification and ongoing
monitoring helps confirm that the validated state remains under control.
WHO guidance on validation describes a life-cycle approach and emphasises that quality should be designed and built into the product rather than expected to be achieved only through final
inspection. The FDA process validation guidance also describes process design, process qualification and continued process verification as connected stages.
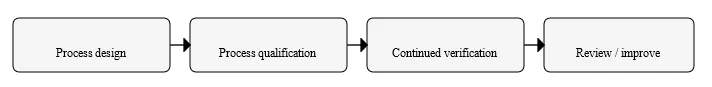
Figure 2: Simplified Lifecycle Model for Process Validation.
Review / improve
6.1 Process validation
Process validation demonstrates that a manufacturing process can consistently deliver product meeting its predetermined quality attributes. The FDA lifecycle model is commonly described in three stages: process design, process qualification and continued process verification. Process design builds understanding using development and scale-up knowledge. Process qualification evaluates the facility, utilities, equipment and process under defined conditions. Continued verification uses routine data to confirm that the process remains in a state of control.
6.2 Cleaning Validation and Contamination Control
Cleaning validation provides documented evidence that an approved cleaning procedure can consistently reduce product residues, cleaning agents and relevant contaminants to justified acceptable levels. It is especially important when shared equipment is used for different products. Cleaning verification may use routine testing or other controls to confirm that cleaning remains effective; the terms should be defined consistently in the site’s quality system.
6.3. Cleaning method development
Development considers the product’s solubility, potency, toxicity, batch size, equipment design, contact surfaces, cleaning agent, time, temperature, mechanical action and rinse characteristics. Hardto-clean locations such as gaskets, valves, dead legs and transfer lines deserve attention. The worst case product or equipment is selected using a documented rationale, not convenience. Manual cleaning may have greater operator variability and therefore needs clear instructions and appropriate training.
6.4. Sampling and analytical methods
Common sampling approaches include swab sampling of defined surface areas and rinse sampling where direct access is difficult or a rinse is representative. Recovery studies establish how efficiently residues can be recovered from the sampled surface. The analytical method must be sufficiently sensitive and suitable for the residue and matrix. Sampling locations should reflect risk and equipment geometry; a convenient location alone may not represent the hardest-to-clean area.
6.5. Acceptance limits and documentation
Acceptance limits should be scientifically justified using relevant health-based exposure limits, product-specific factors, process capability and applicable regulatory expectations. Visual cleanliness is useful but cannot replace analytical evidence where testing is required. The validation package should identify equipment, products, cleaning steps, sampling rationale, method suitability, limits, results, deviations and conclusions. Changes to formulation, equipment, detergent, cleaning cycle or analytical method should trigger impact assessment.
6.6. Contamination control
Contamination control also includes segregation, appropriate HVAC design, controlled personnel and material flows, validated sterilization or aseptic processing where applicable, environmental monitoring and supplier controls. The level of control should be proportional to the product and patient risk. An effective programme links cleaning validation with deviation investigation, maintenance, training and periodic review rather than treating validation as an isolated report.
Cleaning procedures should state the equipment to be cleaned, disassembly requirements, cleaning agent concentration, water quality, temperature, contact time, mechanical action, rinse steps, drying and storage after cleaning. Hold times before cleaning and after cleaning may be important because residues can become harder to remove or equipment can be decontaminated. Operators should be trained to follow the same sequence consistently.
Cleaning validation should also consider the possibility of microbial contamination, cleaning-agent residues and residues from products that are difficult to remove. A successful study should demonstrate that the procedure is reproducible, not simply that one cleaning cycle passed. Routine monitoring, visual checks and periodic review help confirm that validated conditions continue to be maintained.
7. QUALITY BY DESIGN AND PROCESS ANALYTICAL TECHNOLOGY
Quality by Design (QbD) is a systematic development approach that begins with predefined objectives and uses product and process understanding, risk assessment and appropriate controls. It seeks to build quality into the product and process instead of relying only on testing at the end. ICH Q8 describes pharmaceutical development concepts; Q9 supports risk management and Q10 supports a lifecycle quality system.
7.1. QbD elements
A Quality Target Product Profile (QTPP) summarizes the intended product characteristics relevant to quality, safety and efficacy. Critical Quality Attributes (CQAs) are physical, chemical, biological or microbiological properties that should be within an appropriate limit, range or distribution. Critical Material Attributes and Critical Process Parameters are identified through knowledge and risk assessment because they can affect CQAs. Design of Experiments (DoE), multivariate analysis and mechanistic understanding may help evaluate interactions and establish a robust operating space.
7.2. Control strategy
A control strategy combines material controls, process controls, in-process monitoring, finished product testing and lifecycle monitoring to ensure quality. The approach should be proportional to risk and supported by data. QbD does not mean that every process must have a design space or that regulatory flexibility is automatic; any claimed design space and associated flexibility require appropriate evidence and regulatory agreement where applicable.
7.3. Process Analytical Technology
Process Analytical Technology (PAT) is a framework for designing, analysing and controlling manufacturing through timely measurements of critical quality and performance attributes. Tools can include spectroscopic measurements, in-line sensors, chemometrics, multivariate models and automated process control. PAT can improve process understanding and may support real-time release strategies when justified, but it requires suitable measurement systems, representative calibration models, model maintenance and governance.
7.4. Benefits and barriers
Potential benefits of QbD and PAT include reduced variability, earlier detection of process drift, more efficient development, improved knowledge transfer and less reliance on end-product testing alone. Barriers include capital cost, integration with legacy equipment, data management, model lifecycle control, staff skills and regulatory uncertainty for novel applications. Successful implementation starts with a clearly defined problem and a small, measurable use case rather than technology adoption for its own sake.
QbD begins with the patient and intended product performance. Development teams define the target product profile and identify quality attributes that matter to safety and efficacy. They then study how formulation ingredients and process conditions influence these attributes. Risk assessment helps select experiments, and results inform the control strategy. This approach can make scale-up and technology transfer more predictable because the reasons behind process limits are understood.
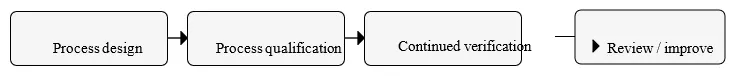
Figure 3: Lifecycle control is supported by product and process understanding.
PAT can provide measurements during processing rather than only after a batch is complete. For example, suitable spectroscopy and validated models may help monitor blend uniformity or moisture. PAT systems need appropriate sampling, calibration, model verification, alarm limits and change control. Models should be checked when raw materials or process conditions change, because a previously reliable relationship may no longer hold.
8. NEED FOR INVESTIGATION
A focused investigation of pharmaceutical QC and QA is necessary because medicine quality has direct implications for patient safety, therapeutic effectiveness and public trust. The existence of written procedures or a final certificate of analysis does not, by itself, demonstrate that every relevant risk has been controlled. A review is useful for understanding how individual technical controls combine into a functioning quality system and where gaps may allow defects to recur.
CONCLUSION:
Quality Control and Quality Assurance are complementary pillars of pharmaceutical quality. QC generates evidence through sampling, measurement and testing; QA ensures that the systems governing design, manufacture, testing, release and distribution are planned, documented and effective. GMP provides the operational foundation, while regulatory authorities establish and enforce requirements appropriate to their jurisdictions. Good documentation and data integrity make decisions traceable and auditable. Qualification, calibration and validation establish confidence in equipment, instruments, processes, methods and cleaning procedures. Process validation must continue into routine manufacture through monitoring and review. Analytical procedure development and validation should be aligned to intended use and current ICH guidance. QbD and PAT can deepen process understanding and enable more timely control, while audits, risk management and CAPA promote continual improvement.
FUTURE PERSPECTIVE:
Future progress will depend on risk-based lifecycle oversight, stronger data governance, improved analytical capabilities, well-designed digital systems, resilient supply chains and an organizational culture that places patient protection ahead of short-term output. For students and practitioners, the key lesson is that quality is created by the combined performance of people, processes, equipment, materials and information, and must be maintained throughout the medicine’s lifecycle.
REFERENCES




Jay Thorat, Snehal Fand, Shital Thorat, Bhavana Tonde, A Comprehensive Review of Quality Control and Quality Assurance in the Pharmaceutical Industry, Int. J. of Pharm. Sci., 2026, Vol 4, Issue 11, 3650-3660. https://doi.org/10.5281/zenodo.24412888
 10.5281/zenodo.24412888